Short answer
Pulsatile tinnitus is a rhythmic noise in one or both ears that beats in time with your heart. Unlike the more common high-pitched ringing tinnitus, it is usually caused by a vascular issue: a change in blood flow near the ear that you can actually hear. Most causes are not dangerous, but some are very treatable, and a few are important not to miss. The right next step is an assessment by a clinician used to looking for vascular causes.
Three things to take away
- Pulsatile tinnitus is almost always vascular. A standard brain MRI is not designed to find every vascular cause, and many are missed, even by experienced radiologists.
- “Your scans were normal” is not the end of the story. Targeted vascular imaging, interpreted by a clinician who is looking for these causes specifically, often picks up what a routine scan misses.
- Some forms are very treatable. A small but important subset of patients benefit from a targeted procedure, provided the cause is identified first.
A note from New Delhi

This guide was updated after I spoke at NICE Live 2026 in New Delhi in September, where I had the chance to discuss the current options for pulsatile tinnitus and how we are improving the workflow for investigating venous causes, from the first clinic visit through to venography and pressure measurement. The talk’s starting point was a familiar story: a patient hears the whoosh every night, and nobody owns the problem. They go from ENT to audiology to neurology to imaging, and each loop takes months. Properly imaged, most pulsatile tinnitus has an identifiable cause, and venous causes are the largest treatable group. The bottleneck is the workflow, not the anatomy.
Colleagues from around the world are working on the same problem, and a new international paper on how cerebral venography and manometry should be done was part of the discussion. The sections “How the pathway is changing” and “What may change next” below come from that talk.
Every day is a school day. We are all still learning how to improve the outcomes for these patients, and the pathway described below reflects where that thinking has got to.
Why this matters
Most tinnitus is non-pulsatile: a hiss, ring or buzz with no rhythm. Pulsatile tinnitus is different. People describe it as a whoosh, swoosh or thump that lines up with their pulse. It can be louder at night, when lying down or after exercise, and it sometimes changes when you turn your head, hold your breath or press on the side of your neck.
Many patients arrive having been told their MRI was normal. That can be reassuring, but a standard brain MRI is designed to look at the brain itself, not at the fine vascular anatomy that produces pulsatile tinnitus. Vascular causes are commonly missed in this group, even by experienced radiologists, because nobody was specifically looking for them. That gap is the reason this article exists.
What you are actually hearing
Pulsatile tinnitus is the sound of turbulent or unusually loud blood flow being conducted to the inner ear. Smooth flow through a healthy vessel is silent. When the calibre, direction or wall of a vessel changes, the flow becomes turbulent, and the bones around the ear conduct that noise inward.
Two patterns are worth knowing:
- Synchronous with your pulse. The classic pattern. Almost always vascular.
- Synchronous with breathing or another rhythm. Usually not vascular. It can come from the muscles of the middle ear or palate (middle ear myoclonus). Different cause, different work-up.
The rest of this article focuses on pulse-synchronous tinnitus.
Causes: venous (the commonly missed ones)
In adults seen in a specialist clinic, venous causes are common, and they are precisely the group most often missed on routine imaging. The main culprits include:
- Venous sinus stenosis. Narrowing of one of the venous sinuses in the skull (often the transverse or sigmoid sinus). Turbulent flow at the narrowing produces the noise.
- Jugular bulb diverticulum. A small outpouching of the jugular bulb, which sits next to the inner ear.
- Anomalous emissary veins. Connecting veins inside and outside the skull, occasionally running close enough to the ear to be heard.
- Dehiscent jugular bulb. Where the thin bony plate between the jugular bulb and the inner ear is missing.
These are anatomical findings. Many are entirely treatable when they are clearly responsible for symptoms.
Causes: arterial
- Atherosclerotic disease of the carotid or vertebral arteries, with turbulence at a narrowing.
- Carotid or vertebral artery dissection, a tear in the artery wall, sometimes after minor trauma.
- Fibromuscular dysplasia, a less common cause of arterial irregularity.
- An anomalous arterial course near the middle ear.
Causes that are important not to miss
Two diagnoses always sit on the differential because they can need active treatment:
- Dural arteriovenous fistula (dAVF). An abnormal connection between an artery and a vein in the lining of the brain. Some types carry a stroke or bleeding risk and need treatment.
- Idiopathic intracranial hypertension. See below.
These are not the most common causes, but they are part of why a single normal MRI is not the end of the assessment.
A standalone note on idiopathic intracranial hypertension (IIH)
IIH is raised pressure of the fluid around the brain. Pulsatile tinnitus can be one of its earliest symptoms, sometimes the only symptom. It is usually associated with headache, occasionally with visual symptoms, and it is more common in younger women, often with weight gain as a contributing factor. The vascular sign on imaging is frequently narrowing of the venous sinuses, picked up on the right scan.
The reason IIH deserves its own paragraph is that it is treatable, and missing it has consequences for vision. If your pulsatile tinnitus comes with headache, visual disturbance or symptoms that get worse when you lie down or strain, it is worth specifically asking whether IIH has been considered.
Why “your scans were normal” can be misleading
Standard brain MRI is not specifically designed to look at:
- The detailed anatomy of the venous sinuses.
- Pressure gradients across a sinus narrowing.
- Subtle dural arteriovenous fistulas.
- Variant emissary veins or jugular bulb anatomy.
- Fine-detail arterial wall changes.
Finding a vascular cause of pulsatile tinnitus often needs targeted imaging: a properly tailored MR venogram, CT angiogram or, in selected cases, a catheter angiogram with venous manometry. The point is not that one scan is “the right scan”, but that the assessment needs to be guided by a clinician familiar with these conditions.
How specialists measure tinnitus severity
Before a clinic appointment, two structured scoring tools help characterise what you are experiencing and how much it affects you:
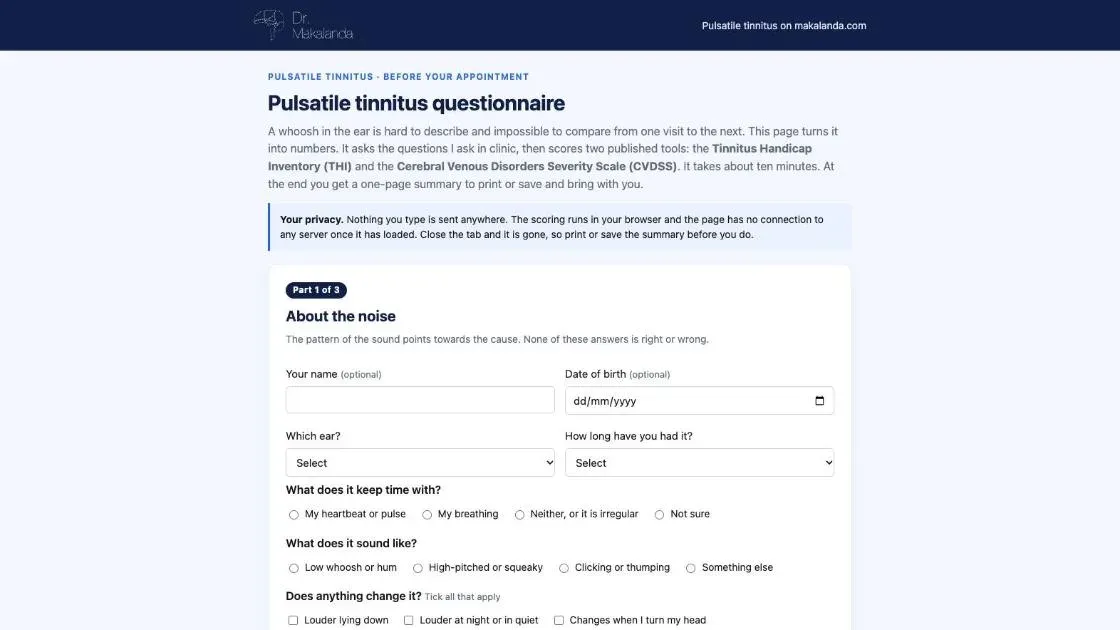
- Tinnitus Handicap Inventory (THI), Newman et al, 1996. Twenty-five questions about the impact of tinnitus on daily life. Scored from 0 to 100. The higher the number, the greater the handicap.
- Cerebral Venous Disorders Severity Scale (CVDSS), Fargen et al, 2025. A short multidomain score covering headache, cognitive dysfunction, tinnitus, dizziness, visual symptoms, involuntary motor episodes and disability. Mild 0 to 5, moderate 6 to 12, severe above 12.
Both are completed quickly. Bringing the completed scores to your appointment makes the consultation more useful: we spend less time on inventory questions and more time on what matters to you.
What assessment may involve
- Pre-consultation questions on the side, onset, modifiers and triggers of the noise, plus the THI and CVDSS scores above.
- Clinical examination, including listening over the head, neck and around the ear for an audible bruit.
- Audiology or ENT review, when a middle or inner ear cause is suspected.
- Targeted vascular imaging: a tailored MR venogram, CT angiogram or catheter angiogram, depending on what the rest of the assessment suggests.
- Venous manometry, in selected cases where a venous sinus narrowing is found, to measure the pressure gradient and decide whether the narrowing is clinically meaningful.
Treatment depends on cause
- Venous sinus narrowing with a meaningful pressure gradient. Some patients benefit from venous sinus stenting. Outcomes can be good when patient selection is right; the procedure carries risks that need to be weighed.
- Jugular bulb anomalies. Selected cases may be amenable to endovascular treatment. Many do not need treatment; reassurance and clear explanation are sometimes enough.
- Dural arteriovenous fistulas. Most require treatment, with urgency depending on drainage pattern.
- Arterial causes. From medical management of atherosclerosis to endovascular treatment of a dissection.
- IIH. Lifestyle measures, medication and in some cases procedural treatment.
- Reassurance and watchful waiting. Where the cause is benign and the symptom bearable, the right answer is sometimes to do nothing, but to explain clearly why.
There is no single “best treatment”. The right approach depends on the cause, how much it bothers the individual and the risk-benefit balance for that person.
How the pathway is changing
Until recently, treating a venous cause took two hospital visits. The first was an awake venogram to measure the pressure across the narrowing. If the gradient justified a stent, the patient came back for a second admission under general anaesthetic, often weeks or months later, with a second puncture, a second consent and a wait for an anaesthetic list. The stents were designed for arteries and needed a large delivery catheter through a vein in the neck, and the pressures at the time of stenting were no longer the ones measured at the first visit.
The workflow I described in New Delhi closes that gap. The aim is one decision at each step and, for the right patient, one sitting for diagnosis and treatment.
- Triage in clinic. A structured questionnaire (the THI and CVDSS scores above), a careful history and an examination that includes gently pressing on the neck vein on the affected side. If that silences the noise, a venous cause is likely. A low-pitched, positional noise that compresses points to venous outflow. A high-pitched noise with an audible bruit points to a fistula and goes straight to angiography.
- One scan. A dual-phase CT angiogram and venogram answers most of the questions in a single study: sinus narrowing, bony defects, jugular bulb anatomy, emissary veins and a screen for fistula. MR venography is added where IIH is suspected. Catheter angiography is kept for fistulas and genuine treatment candidates.
- One sitting, awake. When the scan shows a venous target that fits the symptoms, the patient is booked onto an awake day-case list. Through a vein in the arm, under local anaesthetic and light sedation, I measure the pressures and, if the gradient confirms the cause, place the stent in the same session. Because the patient is awake, I can check that the noise has gone before the stent is finally released. Most go home the same evening.
- Afterwards. Two antiplatelet medicines for three months, then imaging follow-up.
Lower-profile stents have made the awake, arm-access approach practical: the delivery catheter is now narrow enough to avoid a neck puncture and a general anaesthetic. In our own series at The Royal London Hospital, 63 venous sinus procedures since 2020, pulsatile tinnitus improved in about nine out of ten patients and recurrence was uncommon, lowest when the noise was the main reason for treatment. Those are audit figures from one team, not a promise for any individual, and I go through the risks and the likely benefit for your anatomy at the consultation.
What may change next
Several developments are in trials or early use. None is routine yet, and I mention them so you know the direction of travel rather than as options to ask for today.
- Purpose-built venous sinus stents. Every stent used in the sinuses so far was designed for an artery. Stents built for the sinus, with a radial force tuned to a vein and lengths up to 80 mm, are now in pivotal trials in Europe, including studies in IIH and a dedicated pulsatile tinnitus trial that has been recruiting since late 2025. The early series look encouraging.
- Stenting against shunt surgery in IIH. A UK trial is comparing venous sinus stenting with a CSF shunt for IIH that has not responded to medical treatment. Its result will shape how IIH is managed, and pulsatile tinnitus with it.
- Non-invasive pressure measurement. Four-dimensional flow MRI and photon-counting CT may let us estimate the pressure gradient without a catheter, so that only patients likely to benefit go on to venography.
- Treating everything in one visit. The awake one-stop procedure is already possible for selected patients. As the stents and imaging improve, I expect it to become the standard route rather than the exception.
When to seek specialist advice
It is sensible to ask a GP for further assessment if:
- The noise has been present for more than a few weeks.
- It is one-sided.
- It is loud enough to interfere with sleep, concentration or quality of life.
- It is associated with hearing loss, vertigo, headache, visual changes or recent neck pain or trauma.
Seek urgent advice (NHS 111 or A&E) if pulsatile tinnitus appears suddenly with new neurological symptoms: severe headache, weakness, speech difficulty, vision loss or after head or neck injury.
A second opinion is reasonable
If you have been told your scan is normal but the noise is persistent and bothering you, a focused vascular opinion is reasonable. The aim is not to over-investigate. It is to make sure the small but important group of patients with a treatable cause are not missed.
For patients considering a second opinion, the second opinion page explains the process. The pulsatile tinnitus page describes the assessment pathway in more detail.
Frequently asked questions
Is pulsatile tinnitus dangerous?
For most people, no, but it can occasionally point to a treatable condition. The reason to investigate is to make sure the smaller number with a treatable cause are identified.
Why is my pulsatile tinnitus worse at night or when I lie down?
Background noise drops at night, so the sound is easier to hear. Lying down also changes venous return from the head, which can genuinely increase the volume of venous causes.
Should I see an ENT or a neuroradiologist?
Often both. ENT is essential for middle and inner ear causes and audiology. Vascular causes, which are common in this group, sit naturally with an interventional neuroradiologist. The pathways overlap.
Can pulsatile tinnitus be cured?
Some forms can. Venous sinus narrowing with a pressure gradient, certain dural arteriovenous fistulas and selected jugular bulb anomalies can sometimes be treated, with the noise resolving or becoming much quieter.
My MRI was normal. Should I push for more tests?
If the symptom is persistent, one-sided or interfering with daily life, yes. It is reasonable to ask for an opinion from a clinician used to assessing pulsatile tinnitus. A normal standard MRI does not rule out a vascular cause.
This article is for general educational information and is not a substitute for personalised medical advice. If you have symptoms or concerns, please seek advice from an appropriately qualified clinician. For sudden severe headache, new neurological symptoms or symptoms after head or neck injury, seek urgent medical advice via NHS 111 or attend A&E.